AstraZeneca’s camizestrant plus a CDK4/6 inhibitor gains FDA approval for ESR1-mutated HR-positive, HER2-negative advanced breast cancer.
AstraZeneca’s camizestrant (Etcamah) combined with a CDK4/6 inhibitor has received FDA approval for adults with HR-positive, HER2-negative locally advanced or metastatic breast cancer after an ESR1 mutation emerges during first-line aromatase inhibitor and CDK4/6 inhibitor therapy.
AstraZeneca’s camizestrant has gained FDA approval for a biomarker-guided treatment strategy that switches endocrine therapy before radiographic disease progression in patients whose tumours develop ESR1 mutations during first-line treatment.
The approval covers camizestrant in combination with abemaciclib, palbociclib or ribociclib and is based on results from the Phase III SERENA-6 trial (NCT04964934). In a planned interim analysis, the regimen reduced the risk of disease progression or death by 56% versus continued aromatase inhibitor therapy, with a hazard ratio of 0.44 (95% CI, 0.31-0.60; p<0.00001). Median progression-free survival (PFS) reached 16.0 months versus 9.2 months.
Targeting endocrine resistance before progression
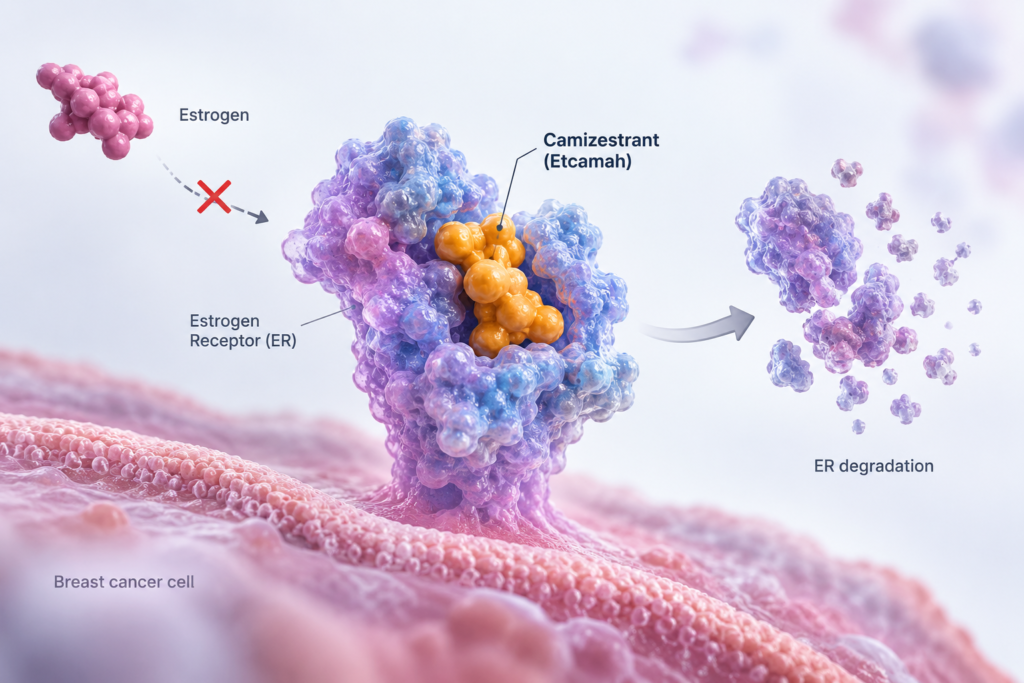
Camizestrant is an oral next-generation selective estrogen receptor degrader (SERD) and complete estrogen receptor antagonist. It is administered once daily at a recommended dose of 75 mg when combined with a CDK4/6 inhibitor.
The strategy addresses a major mechanism of acquired endocrine resistance in HR-positive breast cancer. ESR1 mutations can emerge during aromatase inhibitor treatment and activate estrogen receptor signalling despite estrogen deprivation. Approximately 30% of patients with endocrine-sensitive HR-positive disease develop these mutations during first-line therapy before clinical or radiographic progression.
SERENA-6 tested whether detecting these mutations through circulating tumour DNA (ctDNA) could enable clinicians to change endocrine therapy while the disease remained clinically controlled.
SERENA-6 supports early treatment intervention
The double-blind, randomised Phase III trial enrolled 315 adults with HR-positive, HER2-negative advanced breast cancer receiving first-line aromatase inhibitor plus CDK4/6 inhibitor therapy. Patients underwent ctDNA monitoring alongside routine tumour imaging every two to three months.
When an ESR1 mutation emerged without evidence of disease progression, patients were randomised to switch from their aromatase inhibitor to camizestrant while continuing the same CDK4/6 inhibitor, or to remain on their existing aromatase inhibitor regimen.
A subsequent pre-planned analysis also showed a significant PFS2 benefit. Median PFS2 was 25.7 months with camizestrant versus 19.1 months with standard endocrine therapy (HR, 0.63; 95% CI, 0.46-0.86; p=0.00373). Overall survival remained immature but favoured camizestrant (HR, 0.87; 95% CI, 0.57-1.30), and the trial will continue to assess OS.
The safety profile remained consistent with the known profiles of camizestrant and the CDK4/6 inhibitors. No new safety concerns emerged, while treatment discontinuations were low and similar between groups.
FDA also clears companion diagnostic
The FDA approval coincides with clearance of a companion diagnostic that detects emerging ESR1 resistance mutations in ctDNA. SERENA-6 represents the first global registrational Phase III study to use serial ctDNA testing to identify endocrine resistance and guide a treatment change before conventional evidence of progression.
Kevin Kalinsky of Winship Cancer Institute of Emory University said the approach gives clinicians an opportunity to intervene when ESR1 mutations emerge rather than waiting for disease progression, when treatment options may become more limited.
The approval expands a clinical development programme that includes the Phase III SERENA-4 (NCT04711252), CAMBRIA-1 (NCT05774951) and CAMBRIA-2 trials (NCT05952557), which are evaluating camizestrant across additional treatment settings in HR-positive, HER2-negative breast cancer. Camizestrant is already approved in more than 30 countries, including the EU, Japan, Canada and the UK.